Skip to content

Hospital management · 20–50 beds · India

Not another HMS.
The one built for the hospital you actually run.

ErgoHMS models what small Indian hospitals live with every day: the admitted patient with no bed, the drug that is H1 and NDPS at once, the nurse on her third consecutive night. And every feature is published with its real status.

See what's different

ED RX HR QA
Cloud or on-premise · named users included · every module in scope
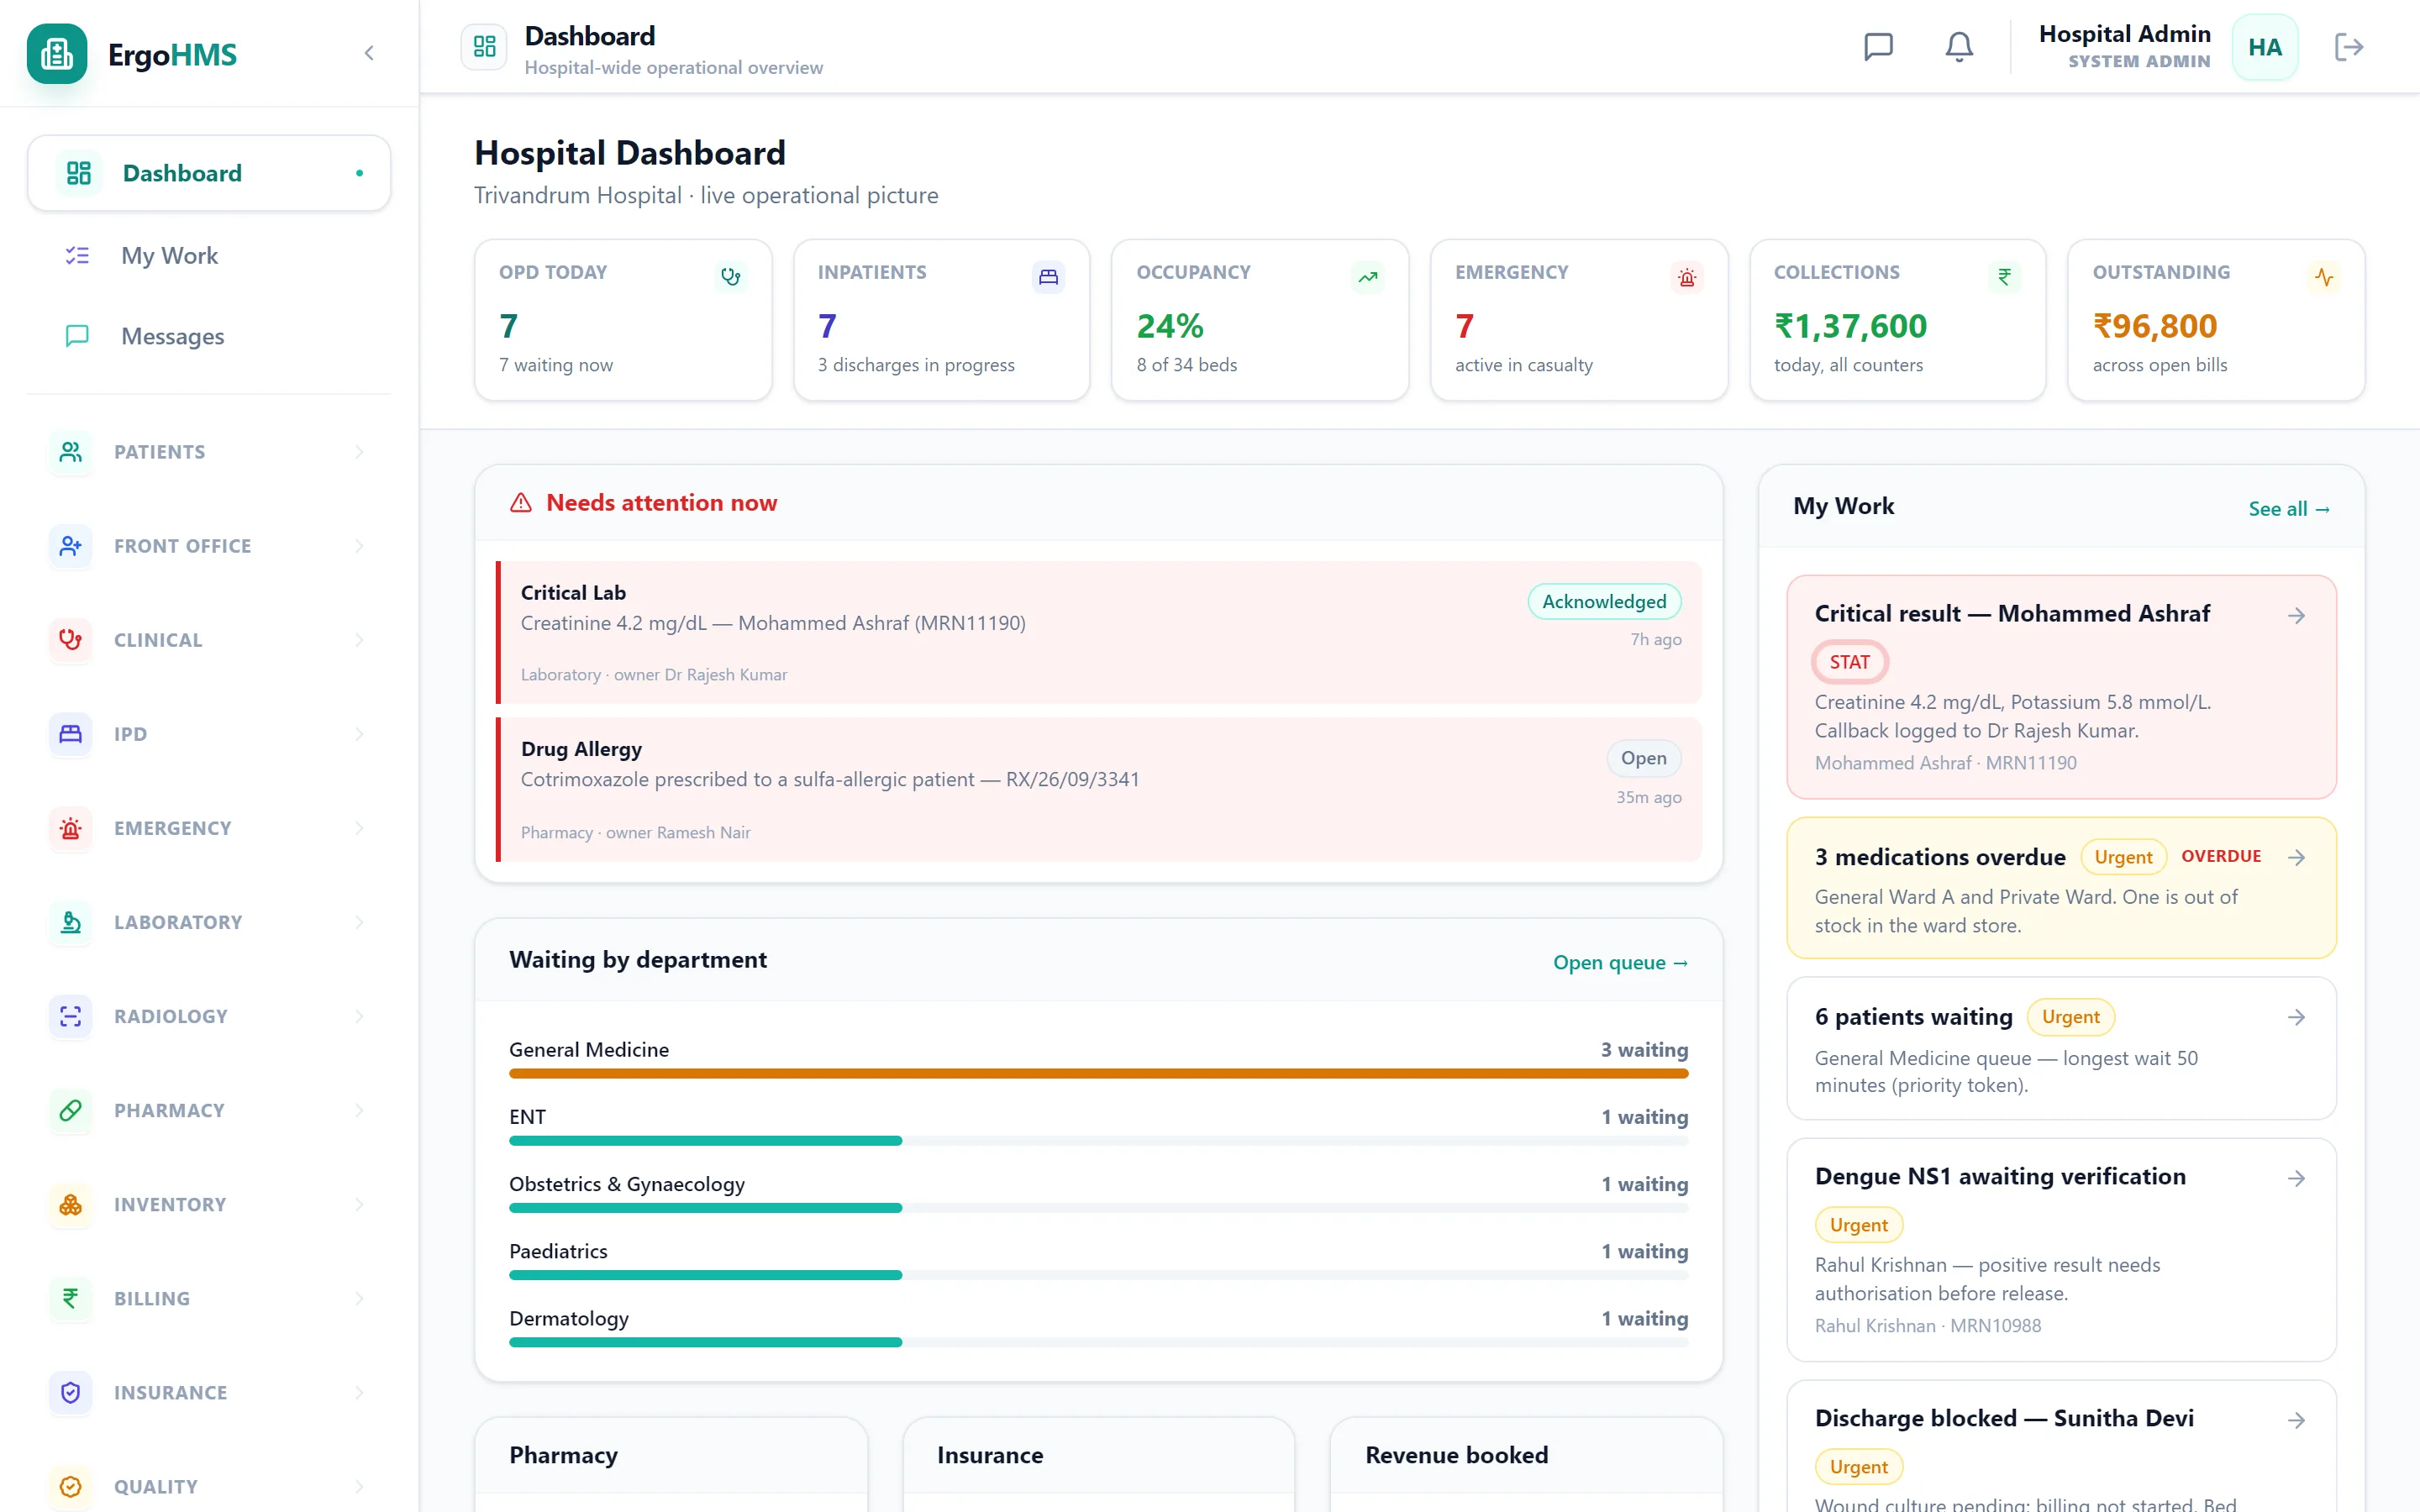
ErgoHMS hospital dashboard with occupancy, queue, alerts and revenue

0

screens, all navigable

0

modules, every plan

0

tests on clinical logic

0

regulatory deadlines in 18 months

Why now

Three regulatory shifts are converging — in exactly this segment.

None of this guarantees a hospital must buy new software this cycle. It is, at minimum, a reason to start the conversation now.

Data protection

Nov 2026

DPDP Consent Manager provisions activate

A one-year phase that brings Consent Manager registration into effect — not a blanket hospital integration deadline. Full compliance is scheduled for May 2027, and section 17(3) allows notified exemptions for certain entity classes.

01

Insurance

Reported

IRDAI three-hour cashless expectation

A published expectation that cashless claims move quickly after discharge authorisation, tied to NHCX. The exact trigger event and current circular still need confirming before we build a compliance claim on it.

02
Accreditation

Reported

NABH Entry Level: a PMJAY incentive is reported

NABH’s revised Entry Level programme is reported to carry a PMJAY incentive for certified hospitals. Chapter count, evidence-period requirements and exact terms are pending verification against the current programme manual.

03

The hard domain calls

Built around the patient the other systems can’t see.

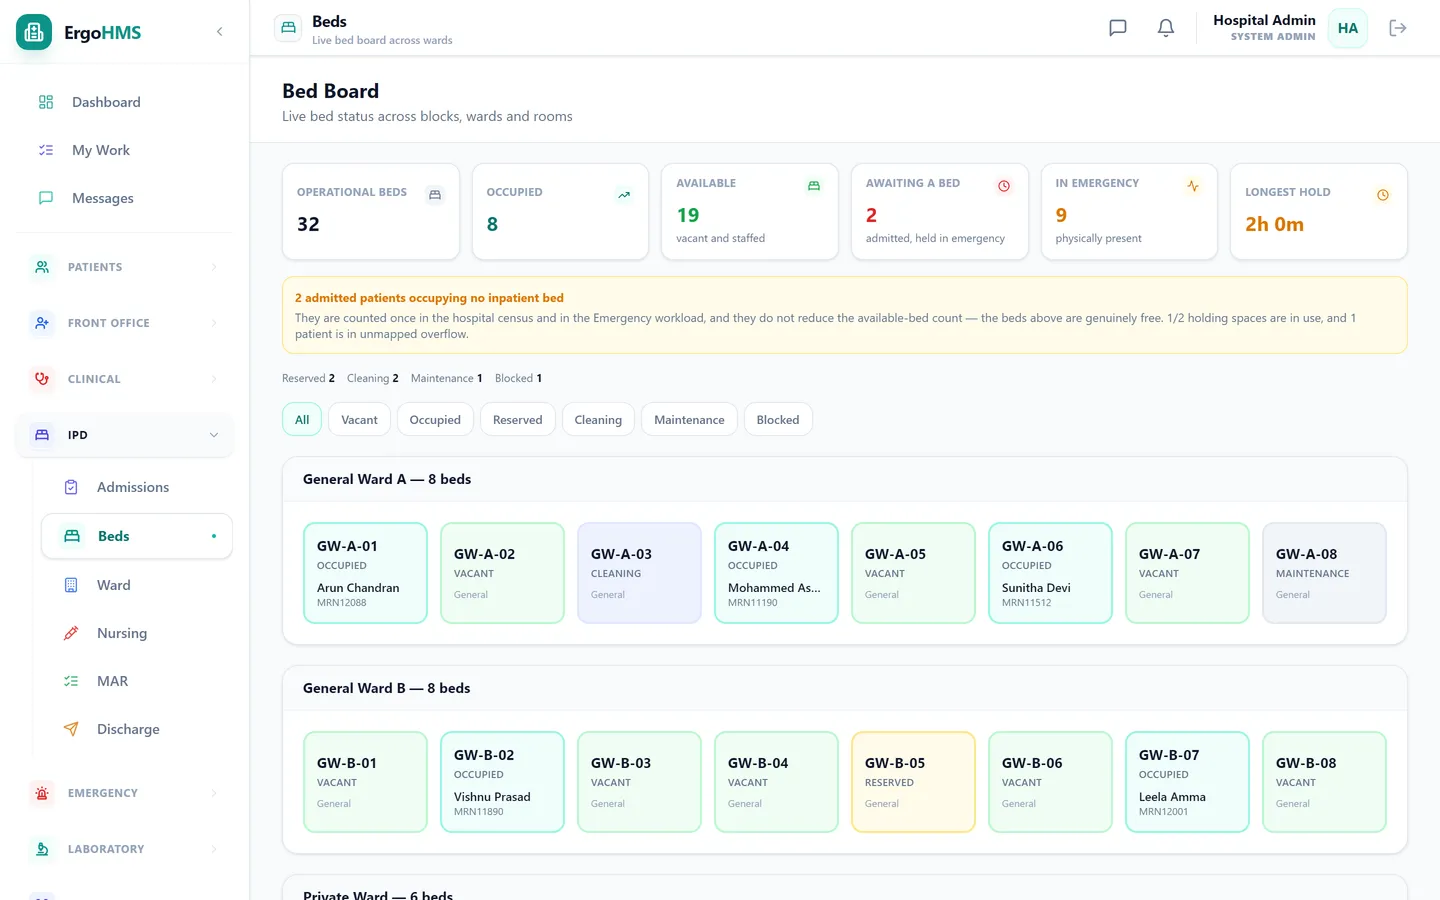
“Admitted, no bed” is a first-class state. A bed is judged for suitability, not counted as available. Anyone who has built Indian HMS hit these walls; this is how we resolved them.

Live 30 tests · five rungs · seven alert conditions

Emergency · Holding

Sneha Mohan MRN12112 · OBG

Admitted, no bed

Boarding for

0h 00m

Escalation

Rung 0/5

60120240360480
  • 1Charge nurse informed
  • 2Bed manager paged
  • 3Duty medical officer
  • 4Medical superintendent
  • 5Divert / admin escalation
Dr Fathima Rasheed Sr. Jincy Paul 7 alert conditions

ED boarding with an escalation clock

Every domain expert knows this patient exists; we did not find a published example of software tracking them this way. Occupied beds and patients-we-are-responsible-for are reported separately, so boarding patients never vanish inside one occupancy percentage.

Live Isolation · sex · paediatric · maternity · capability · staffing

Bed request

Female · 34 · Obstetrics

Needs monitoring · No isolation · Night admission

19 available

Evaluating GW-07

General ward · mixed

1 / 3
  • Isolation not required
  • Sex restriction: female bay
  • Maternity fit
  • Monitoring capability
  • Staffed this shift

Bed suitability, not availability

Many products we reviewed stop at “allocate a bed”. ErgoHMS checks whether the bed is fit for this patient and staffed on this shift — an unstaffed bed is furniture.

Live

MLC as a determination, never an inference

Police arrival raises a trigger; only a named clinician sets status, with a reason. Auto-flagging produces false MLCs — and confirmed ones nobody assessed.

Live

Overlapping drug regimes, effective-dated

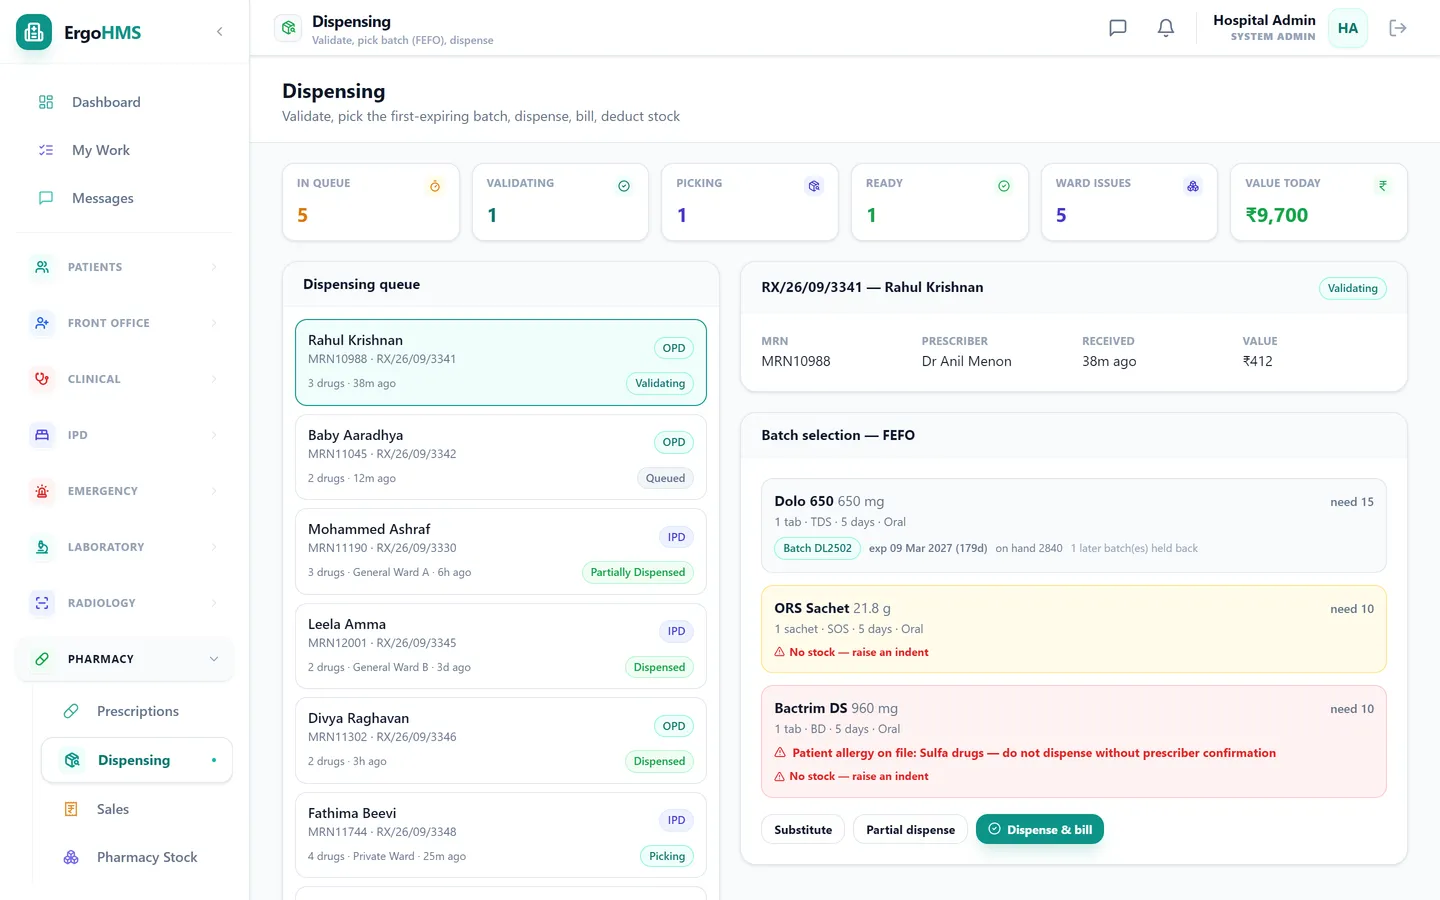
A drug can be H and H1 and NDPS simultaneously, and the same sale is judged correctly before and after a schedule amendment. 24 tests.

Live

Emergency care that is never gated

Casualty forms deliberately don’t require identity, payment or documents. A mandatory field in an ED is a refusal of treatment wearing a validation message.

Six reasons

Why this is not another HMS in the market.

In the order a domain expert should hear them.

01

Three regulatory shifts are converging — in exactly this segment.

DPDP’s principal data-processing obligations are scheduled for May 2027, with Consent Manager registration provisions activating from November 2026 — not a blanket hospital integration deadline, and section 17(3) of the Act leaves room for notified exemptions. IRDAI has published a three-hour cashless-claim expectation tied to NHCX, with its exact trigger still to confirm against the live circular. NABH’s revised Entry Level programme is reported to carry a PMJAY incentive for certified hospitals; exact terms are pending verification.

Reason enough to start the conversation now — not proof that anyone must buy.

02

Most incumbent “AI” reads as marketing copy — though not all of it does.

One “AI-Powered” platform resolves, on its own page, to “AI/ML ready”, “a single data lake” and Alexa integration. Others advertise pharmacy forecasting, resource optimisation or an AI scribe. We have not independently tested any competitor’s deployment, and a vendor’s homepage is not proof either way.

We are building only what our own data supports, and saying plainly where we have not verified a competitor’s claim.

03

The hard domain calls are already made — and they’re the right ones.

Boarding as a tracked state. MLC as a clinician’s determination rather than an inference from arrival mode. Schedule H, H1 and X as overlapping effective-dated regimes instead of one enum.

Anyone who has built Indian HMS hit these walls. We hit them too — here is how we resolved them.

04

The boring eighty percent already exists.

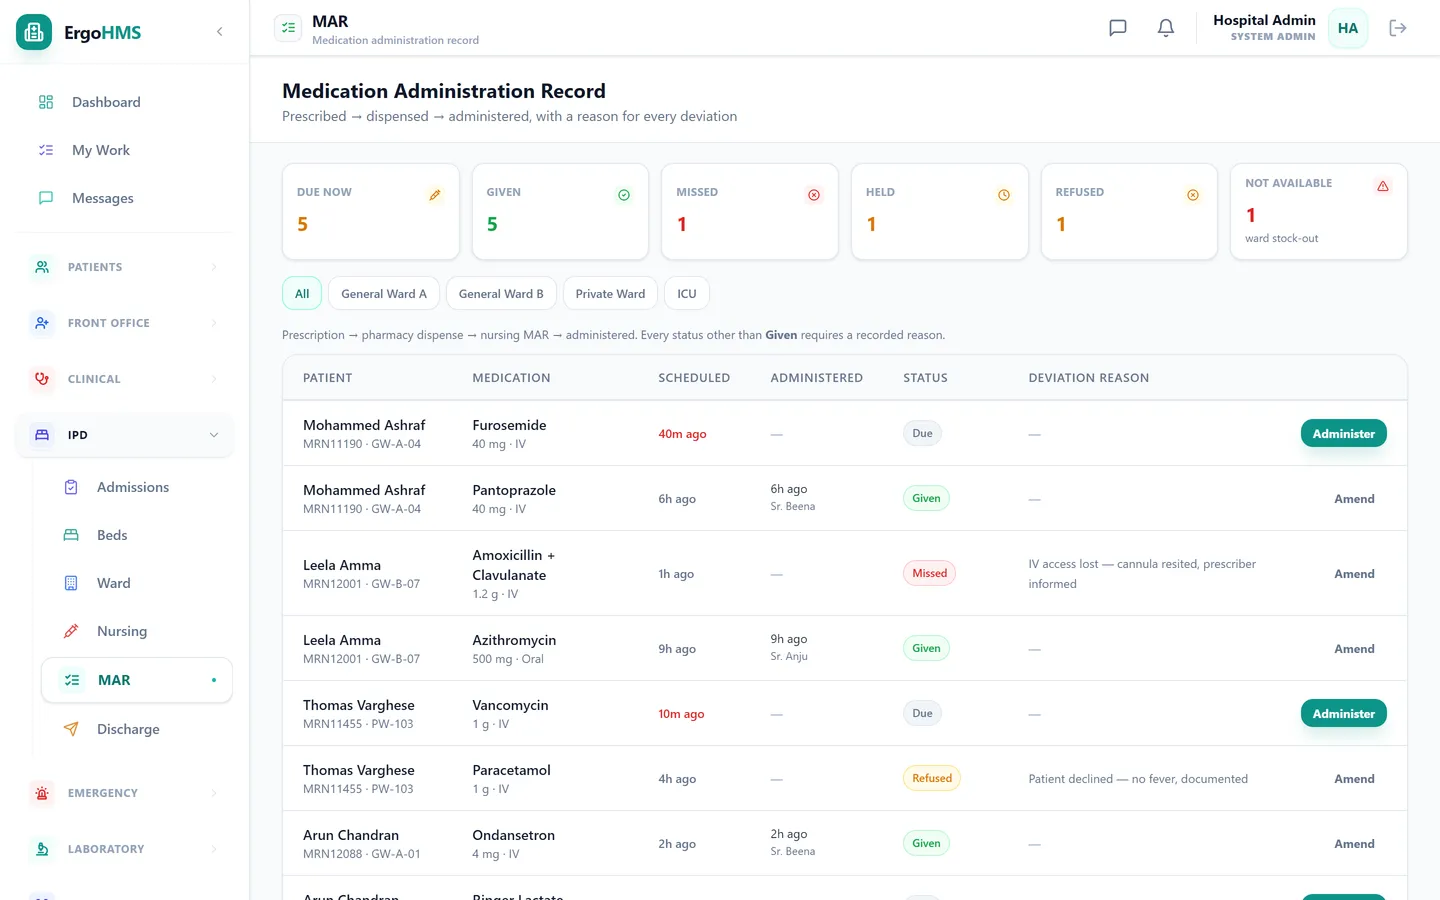
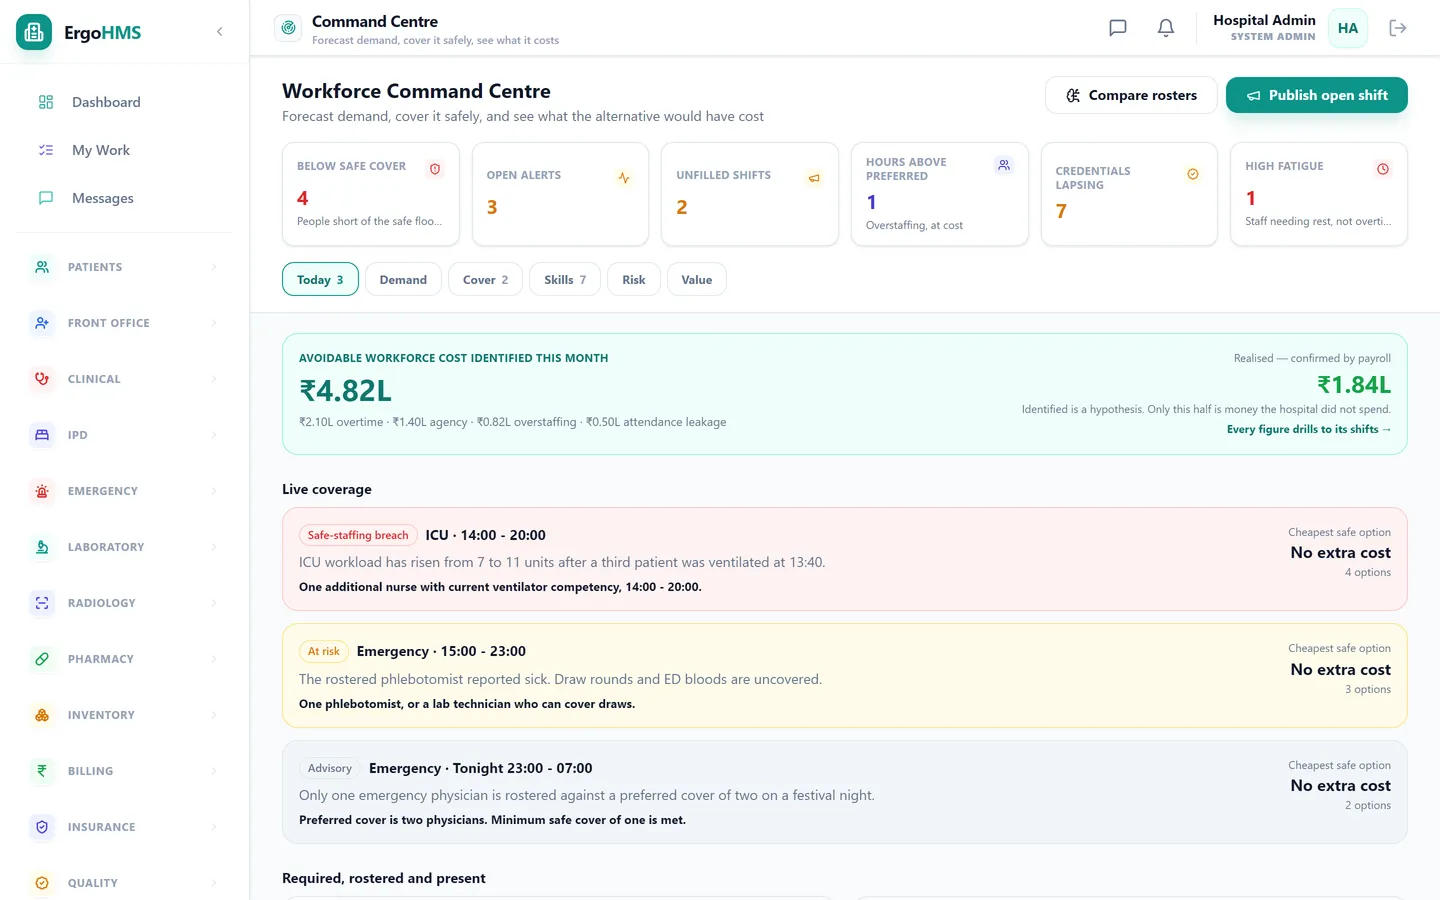
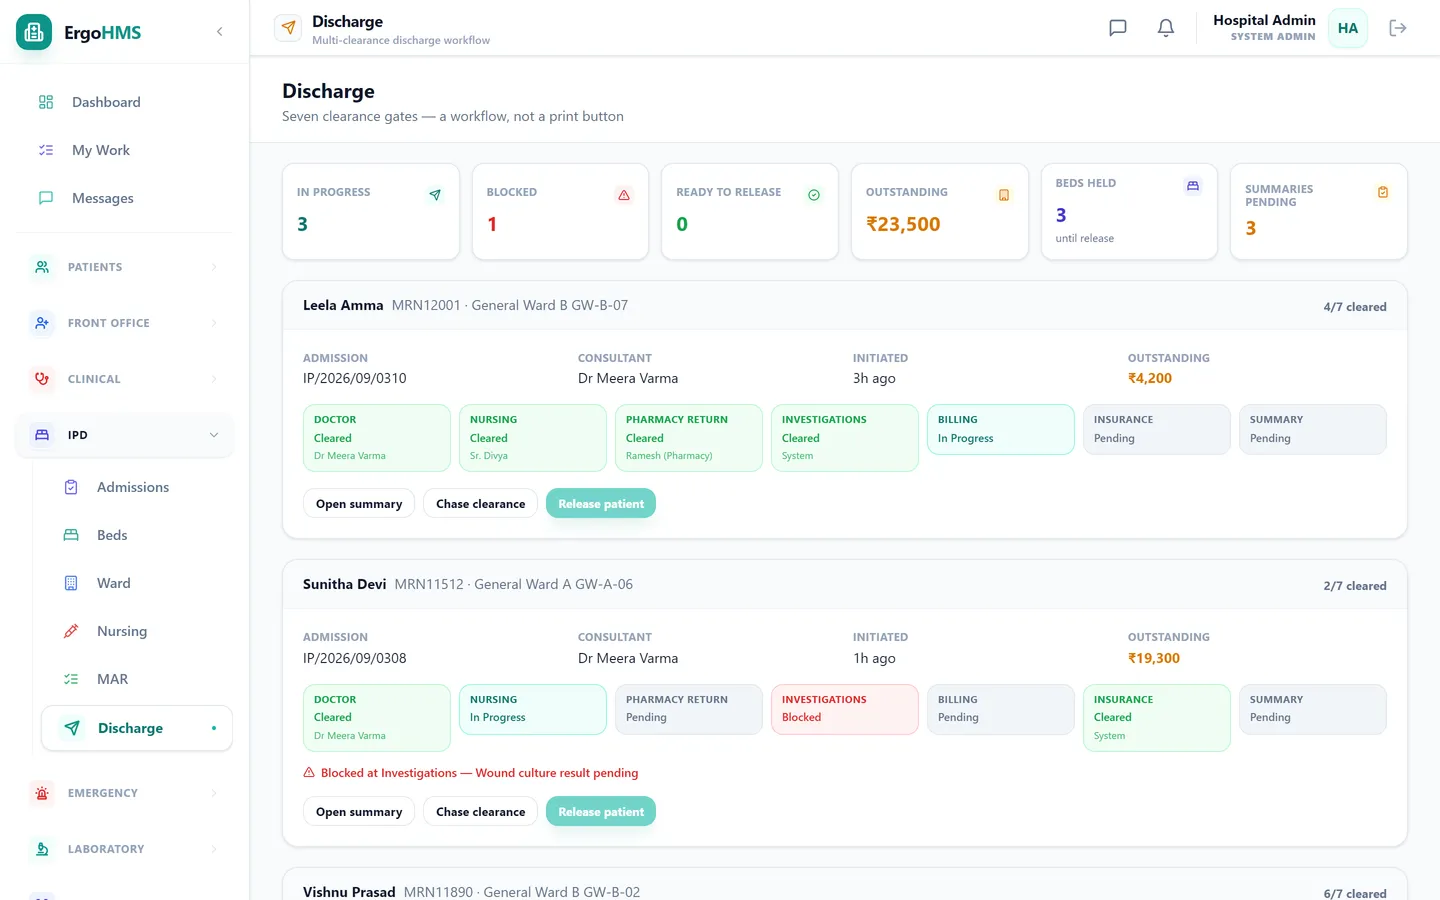
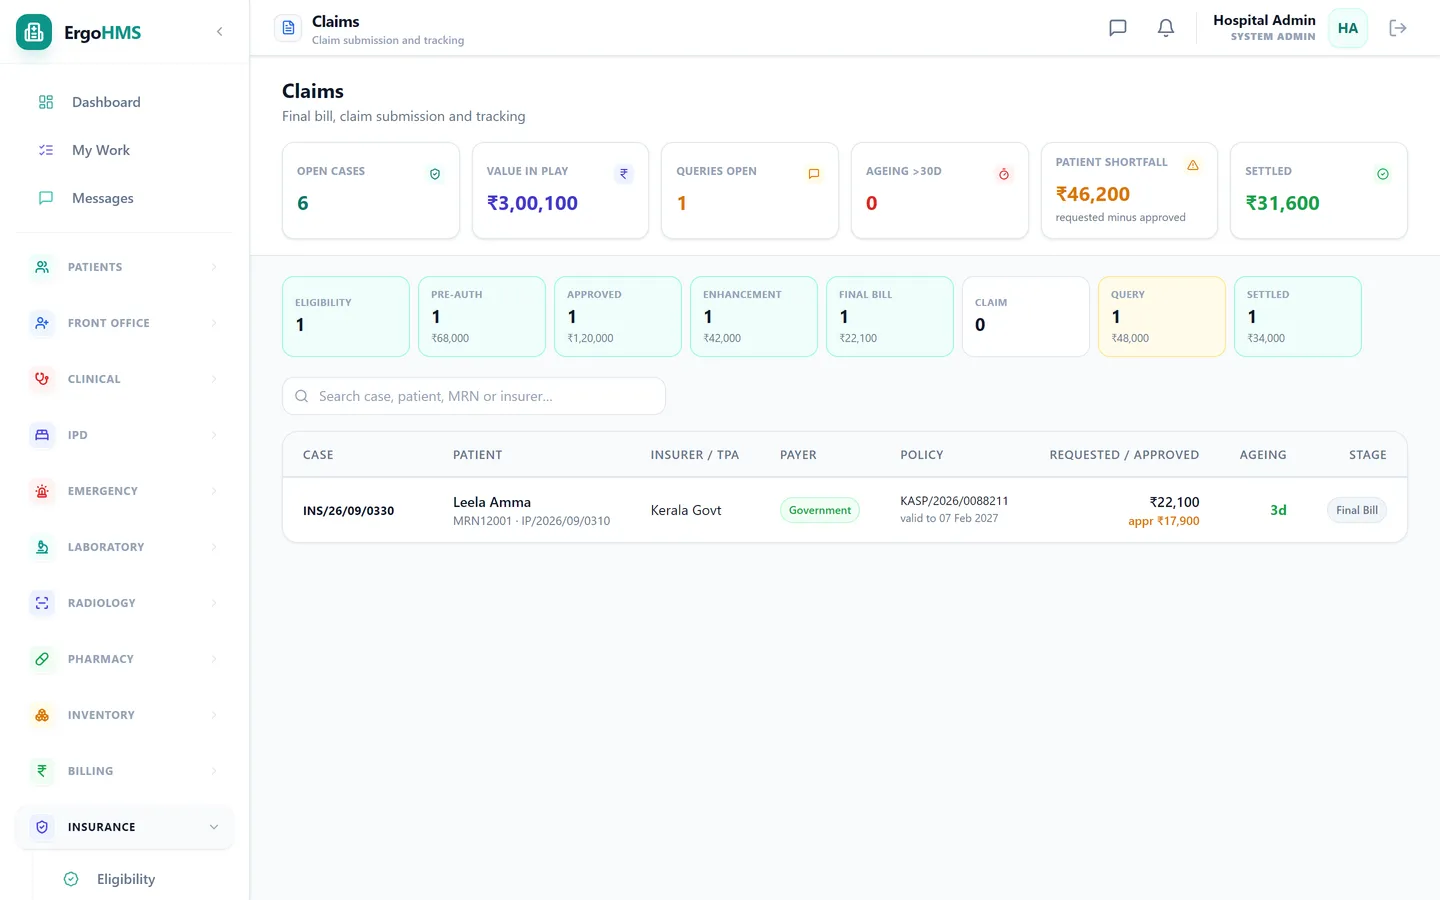
130 screens across 20 modules — OPD, IPD, pharmacy, lab, radiology, billing, insurance, inventory, quality, assets, workforce, security — with 298 passing tests on clinical logic. These are our own reported counts from the current codebase, not an independently audited figure.

Nobody is joining a blank repository and two years of CRUD.

05

The domain model is built to earn a data advantage — once there is data.

Our design captures ED boarding duration, escalation rungs, bed suitability, staff fatigue and credential-to-shift binding as first-class data. Nothing is persisted to a database yet, so no dataset exists to train on — this is the shape it would take once persistence ships and a pilot hospital generates real volume.

AI here would be a consequence of the domain model, not a bolt-on — once there is data behind it.

06

Everything is published with its real status — including the unflattering parts.

Every feature on this site carries Live, Engine, Designed or Proposed. For a hospital deciding whether to trust a vendor for years, a team that publishes its own gap analysis is worth more than one with a better demo.

Read the roadmap. It lists what is not built.

The product

Screens from the demo hospital, not a mock-up.

Trivandrum Hospital: 34 beds, NABH Entry Level, eighteen staff personas. Every screen here is navigable today.

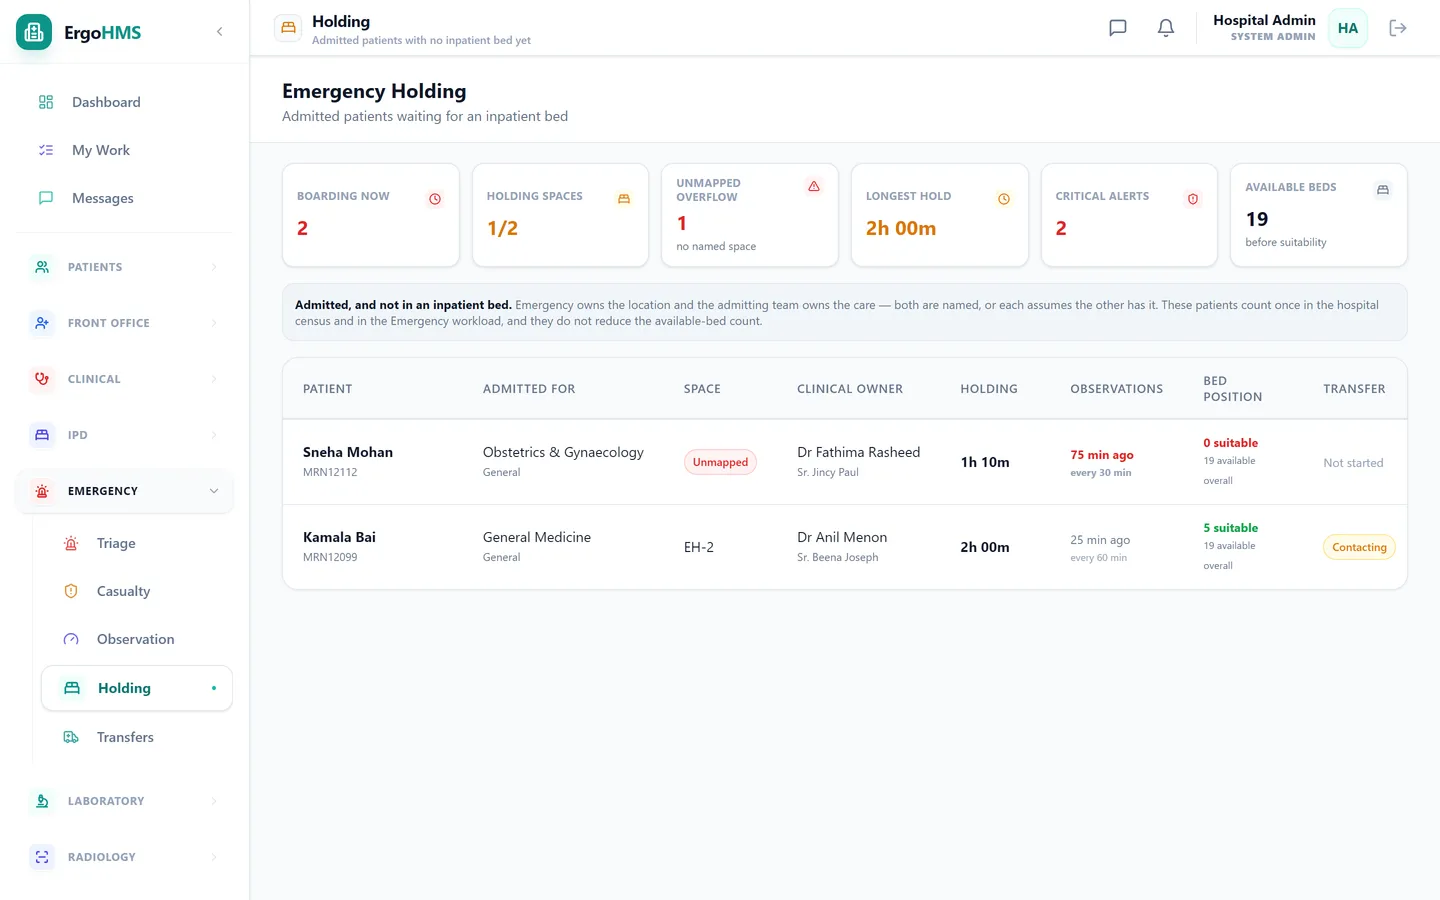
ErgoHMS Emergency Holding screen showing boarding patients, holding times and bed suitability

Admitted, no bed — tracked, timed, escalated. Two patients boarding, one in an unmapped overflow space, the longest at two hours. Seven alert conditions, five escalation rungs, and a census that counts them.

A smiling nurse in blue scrubs with a stethoscope
One person, three desks

Reception at 9, OP billing at 11, pharmacy counter at 2. One shift-worker view instead of three role-shaped silos.

Built for how small hospitals work

Designed for a receptionist who is also billing and also pharmacy.

Small hospitals have no dedicated data-entry operators. The software has to get out of the way — and keep working when the network doesn’t.

  • Never-gated emergency care

    Live

    Identity, payment and documents come after treatment starts.

  • Duplicate detection while typing

    Live

    Name, mobile and ABHA weighted — Use Existing, Continue New or Send for Review.

  • A published click budget

    Proposed

    Admit in three clicks or fewer, record a dose in two. Printed on the features page.

  • Degraded-network mode

    Proposed

    Local-first with sync. Pull the cable mid-demo and keep admitting.

The groundwork

The boring eighty percent already exists.

OPD, IPD, pharmacy, lab, radiology, billing, insurance, inventory, quality, assets, workforce, security. You are not spending two years on CRUD.

Every module, every screen
A hospital reception desk in a bright lobby

Inherited and still useful

Tamper-evident audit trail, e-signatures, document control, CAPA, Report Studio, inventory with batch, expiry and FEFO, GST billing, RBAC — carried over from a mature LIMS.

Published with its real status

Every feature on this site carries Live, Engine, Designed or Proposed.

For someone deciding whether to trust a vendor with years of their hospital, a team that publishes its own gap analysis is worth more than one with a better demo.

0

Live

Works in the product

0

Engine

Engine built and tested, screen not wired

0

Designed

Designed or schema only

0

Proposed

Proposed, not started

The unflattering part

Nothing persists to a database yet. The whole product runs on in-memory state. Persistence is the current milestone.

Read what is not built

See the hospital you actually run, on screen.

A forty-minute walkthrough with the demo hospital: casualty to discharge, pharmacy to claims. Bring the edge cases that broke your last system.

Or try the demo yourself